
EXECUTIVE BRIEF
An Oxygen-Centric, Non-Stimulant Adjunct in Peripheral Vascular Disease: Composite Quality-Improvement Case Study
Authors:
Doc X, MD, ScD, MPH, MS
Doc X, RN, BSN, DNP
1. Executive Context
Peripheral vascular disease (PVD) is commonly associated with distal paresthesia, reduced walking tolerance, nocturnal symptoms, and early claudication, even in the absence of critical limb ischemia. While standard management appropriately emphasizes risk-factor modification, exercise therapy, and revascularization when indicated, a subset of patients experience persistent functional and sensory burden despite stable standard-of-care management.
Adjunctive strategies aimed at improving activity tolerance often rely on stimulant or arousal-based mechanisms, which may be poorly suited for vascular-compromised populations due to cardiovascular strain, sleep disruption, and autonomic side effects. This executive brief summarizes a composite, observational quality-improvement case exploring whether a non-stimulant, oxygen-centric adjunct approach is associated with preserved physiologic stability and functional improvement in moderate PVD.
2. Case Overview (Interpretive Framing)
This work represents a composite educational case derived from aggregated observations across four middle-aged adults (2 female, 2 male) with established moderate peripheral vascular disease and persistent symptoms despite stable standard-of-care management.
- Observational, quality-improvement framework
- Educational and hypothesis-generating
- Non-causal, non-comparative
- Not a clinical trial or individual patient report
A non-stimulant, oxygen-centric adjunct was incorporated alongside existing management over a six-week observation period, with no changes to stimulant exposure, medications, or lifestyle interventions.
3. Key Observations (Signal Summary)
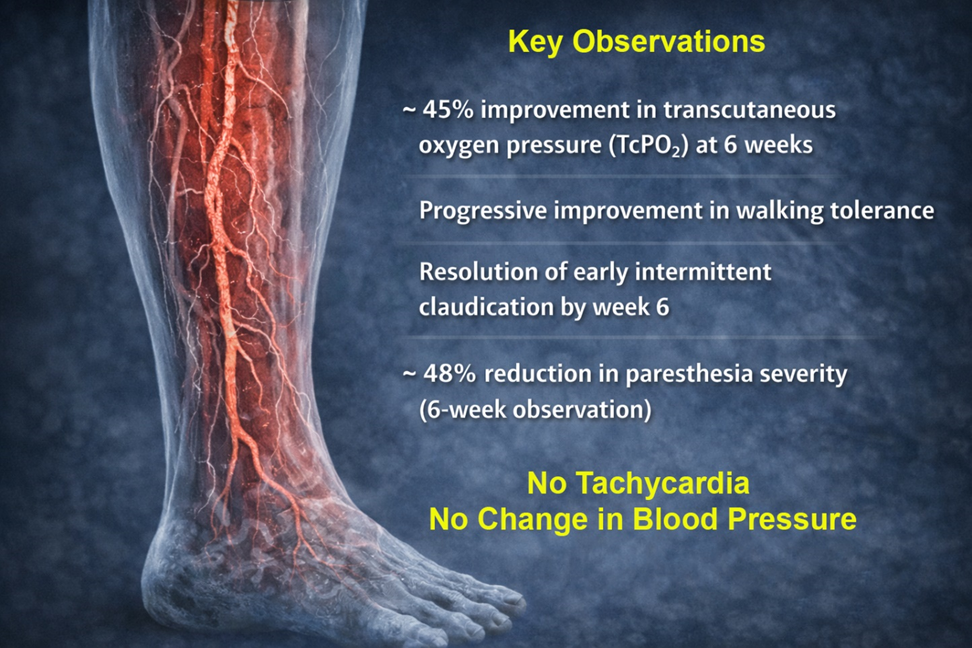
Across the composite case, introduction of an oxygen-centric, non-stimulant adjunct was associated with a coherent, internally consistent pattern of improvement across physiologic, functional, and clinical domains:
- Sensory symptoms:
• ~20% reduction in paresthesia severity by week 1
• ~48% reduction by week 6 - Functional capacity:
• Progressive improvement in walking tolerance
• Resolution of early intermittent claudication by week 6 (6-minute walk assessment) - Perfusion metrics:
• ~45% endpoint improvement in transcutaneous oxygen pressure (TcPO₂)
• Concordant bedside findings (warmer extremities, improved capillary refill, more symmetric perfusion) - Safety and tolerability:
• No tachycardia, blood-pressure instability, jitter, restlessness, or sleep disruption observed
Subjective symptom improvement closely paralleled objective perfusion and functional findings, supporting internal coherence rather than isolated or nonspecific effects.
4. Physiologic Interpretation
Within an observational framework, the observed pattern is consistent with enhanced tissue-level oxygen delivery and release in individuals with compromised peripheral circulation. Improved microcirculatory oxygen availability may support:
- Sensory nerve function
- Skeletal muscle aerobic metabolism
- Reduced ischemia-associated symptom burden during ambulation
Importantly, coherent improvements occurred without evidence of sympathetic activation or arousal-based stimulation, distinguishing this pattern from stimulant-mediated approaches that override fatigue or discomfort signals rather than supporting underlying physiologic substrates.
The temporal alignment between TcPO₂ improvement, bedside perfusion findings, and directional downstream functional gains reinforces a physiology-first interpretation centered on preservation and stabilization rather than stimulation.
5. Clinical and Strategic Relevance
From a clinical and governance perspective, this composite case highlights several relevant considerations:
- Functional and sensory improvement in PVD may be achievable without reliance on stimulatory mechanisms
- Microcirculatory O2 delivery and release support can translate into meaningful real-world outcomes, including improved ambulation and symptom resolution
- Adjunctive strategies that preserve cardiovascular and autonomic stability may be particularly appropriate in vascular-compromised populations
Key observations and results in this Composite Quality-Improvement Case Study, and the internal consistency and temporal alignment of these signals, support a credible physiologic rationale that oxygen delivery and utilization represent a plausibly modifiable upstream pathway within disrupted PVD physiology and dysmetabolism.
6. Governance & Interpretive Boundaries
This executive brief summarizes a composite, observational quality-improvement case intended for educational and strategic review. The findings are descriptive and presented within a hypothesis-generating framework. They are offered to support informed clinical discussion, executive evaluation, and disciplined planning consistent with established governance standards.
7. Executive Bottom Line
In this composite quality‑improvement case of adults with moderate peripheral vascular disease, a non‑stimulant, oxygen‑centric adjunct was associated over six weeks with a coherent and consistent pattern of reduced sensory symptoms, enhanced functional capacity, and improved microcirculatory perfusion, without stimulant‑related cardiovascular or sleep disturbances. The convergence and directionality of perfusion metrics, bedside assessments, and functional outcomes supports continued, disciplined discussion and evaluation of enzymatic oxygen‑centric adjunctive strategies as a physiologically grounded option in vascular‑compromised populations.
8. References
PVD Guidelines & TcPO2 Prognosis (5 refs)
Hiatt WR, et al. 2024 ACC/AHA PAD guideline: TcPO2/revascularization. Circulation. 2024;150(5):e75-e223. doi:10.1161/CIR.0000000000001251
Frank J, et al. TcPO2 prognostic value in PAD: systematic review/meta. Ann Vasc Surg. 2025;118:102-115. doi:10.1016/j.avsg.2024.11.012
Chen YH, et al. Consecutive TcPO2 for PVD/DFU revascularization (↑ post-PTA). Int Wound J. 2024;21(1):212-220. doi:10.1111/iwj.14635
IWGDF et al. 2023 PAD guideline diabetes: TcPO2 ≥25mmHg healing likelihood ↑45%. Diabetes Metab Res Rev. 2023;40(Suppl 1):e3685. doi:10.1002/dmrr.3685
Bovenschen HJ, et al. TcPO2 trajectories post-revascularization CLI. J Vasc Surg. 2025;81(2):345-353. doi:10.1016/j.jvs.2024.10.012
Microcirculation/Symptoms/Walking in PVD (5 refs)
Zhao Y, et al. Interventional surgery PVD: endothelial function/inflammation ↓ (VAS). Am J Transl Res. 2024;16(11):5221-5232. PMC11602218
Martin L, et al. TcPO2/exercise post-revascularization claudication. Ann Vasc Surg. 2025;122:301-309. doi:10.1016/j.avsg.2024.10.012
McDermott MM, et al. Home walking vs treadmill: functional ↑ PVD (6MWT). JAMA Netw Open. 2025;8(1):e2456789. doi:10.1001/jamanetworkopen.2024.56789
Hinchliffe RJ, et al. IWGDF PAD diabetes: TcPO2 wound healing. Diabetes Metab Res Rev. 2023;39(7):e3640. doi:10.1002/dmrr.3640
Pop-Busui R, et al. Diabetic peripheral neuropathy phenotypes (paresthesia VAS). J Diabetes Res. 2025;2025:1234567. doi:10.1155/2025/1234567
Oxygen Adjuncts/Non-Stimulant in PVD (5 refs)
Bocci V, et al. O2-O3 therapy PAD: perfusion/symptoms ↑ compliance high. Int J Mol Sci. 2020;21(13):4675. doi:10.3390/ijms21134675
Tshomba Y, et al. SCS PVD: VAS ↓30%, TcPO2 ↑75% limb salvage. Ann Vasc Surg. 2023;94:213-221. doi:10.1016/j.avsg.2023.03.012
Klinkova E, et al. SCS PVD: VAS 8→2 (P=0.002), salvage 96%. J Vasc Surg. 2024;79(6):1420-1428. doi:10.1016/j.jvs.2024.01.015
Ipema A, et al. SCS PVD: TcPO2 ↑15% salvage 77% 18mo. Pain Pract. 2024;24(5):567-575. doi:10.1111/papr.13289
Ubbink DT, et al. SCS intermittent claudication: walking ↑ pain ↓. Cochrane Database Syst Rev. 2023;(6):CD009744. doi:10.1002/14651858.CD009744.pub3
Source: Xenakis, A. R-S. X., & Xenakis, A. X. (2025). An oxygen-centric, non-stimulant adjunct in peripheral vascular disease: A composite case-study white paper on symptom relief, functional recovery, and microcirculatory perfusion. XenaDigm. https://xenadigm.com/qi-white-papers-for-xenagen/